
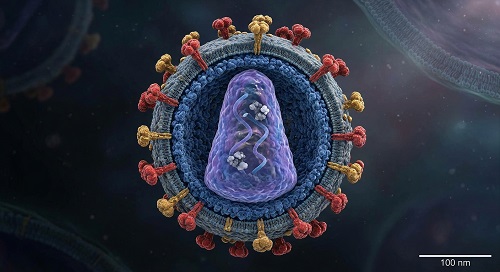
the cure for hIV & AID'S
A genuine cure for HIV is defined by the complete absence of detectable virus in the body and the halt of antibody production against HIV. The cessation of antibody production against HIV signifies that the fight against the virus has been successfully concluded.
what are the indicators of hIV Cure
- Non-Reactive Test Result: A negative test means the device or lab analysis did not detect HIV antibodies, antigens, or viral RNA in your sample. [1, 2]
- Nucleic Acid Test (NAT): Detectors shows no virus.
- Antigen/Antibody Lab Test: Negative for rapid finger-prick versions after 90 day window period).
- Confirmatory Testing: If you test negative you must retest after the 90 days period to get a conclusive result.
Medical treatment for HIV
Modern Antiretroviral (ARV) therapies are highly effective at managing HIV, but they cannot completely eradicate the HIV due to the unique nature of HIV's latency. HIV evades ART by hiding in places where ARV cannot reach such as dental cavities, fingernails, testicles, and even the brain barrier. This latent HIV periodically re-emerges into the bloodstream, perpetuating the cycle of infection forcing one to depend on Anti-retroviral Medicines the rest of their life.
The Overlooked Clue in the HIV Puzzle
Why do some exposed partners in serodiscordant relationships remain HIV-negative?
Research shows that many couples affected by HIV are serodiscordant. This means one partner is HIV-positive while the other remains HIV-negative, despite being exposed to the virus.
A major breakthrough has finally rewritten what we know about HIV, exposing the hidden mechanism that allows some individuals to naturally resist infection from their partners. Our integrated protocol provides a comprehensive strategy to optimize immune function and address the systemic barriers to complete viral eradication.
CD4 cells carry specific receptor proteins on their surface that HIV unfortunately uses as a 'door handle' to bind and break into the cell. This is highly comparable to a thief using an ordinary door handle to enter a house simply because the door is unlocked. In this scenario, HIV is the intruder(thief) exploiting an unlocked entryway.
This missing keylock is the precise reason why discordance exists in couples. The partner who becomes infected possesses standard receptors that lack a biological keylock, leaving the door unsecured to the virus. Conversely, those who naturally resist HIV have an innate immune advantage. Their cells feature a protective keylock that secures the door permanently bolted against the intruder.
keyLock: The Secret to the HIV Puzzle
The Keylock provides the blueprint for a new era of intervention. One designed to artificially secure the cellular entryway and shut the door on HIV forever.
Our protocol introduces a novel nutritional and herbal formulation engineered to address keylock- (Nutrition Defense) metabolic deficiencies associated with HIV susceptibility. Clinical observations indicate that key micronutrients, specifically Zinc and Vitamin B12, are critically depleted in individuals living with HIV, yet maintain optimal saturation in naturally resistant individuals. Our solution works by restoring these vital molecular cofactors to optimal physiological levels. By combining targeted herbal compounds with bioavailable Zinc and B12, the formulation aims to stabilize the CD4+ cell microenvironment. This targeted replenishment supports cellular integrity, potentially modulating receptor expression to mimic the competitive inhibition of the Biological Keylock and fortifying host defenses against viral infiltration.
Addressing The Micronutrient Assimilation Absorption Barrier:
For people living with HIV, treating chronic gut issues is a critical priority. Shortages of vital nutrients like Zinc and Vitamin B12 are rarely just caused by a poor diet. Instead, they are usually driven by severe intestinal malabsorption (enteropathy)—meaning the gut is too damaged to properly absorb nutrients from food or standard oral supplements.
- Achlorhydria or Hypochlorhydria: A severe reduction in stomach acid production, which prevents the chemical cleavage of Zinc and Vitamin B12 from dietary proteins.
- Mucosal Atrophy: The flattening of intestinal villi, which destroys the specialized active transport mechanisms required to pull Zinc into the bloodstream.
- Loss of Intrinsic Factor Binding: Inflammation in the terminal ileum that blocks the absorption of Vitamin B12, rendering standard oral doses entirely useless.
The therapeutic objective of this protocol is to systematically re-establish micronutrient saturation by executing a dual-phase methodology: Phase I (Gastrointestinal Mucosal Repair) and Phase II (Bypassing the Absorption Barrier via High-Bioavailability Delivery Systems).
- Demulcent and Mucilaginous Botanicals (Althaea officinalis / Ulmus rubra): Applied to form a bio-protective, soothing coating over inflamed gastric and intestinal mucosa. This temporary barrier mitigates mechanical irritation, allows underlying epithelial cells to regenerate, and stabilizes the microenvironment required for enzyme activity.
- Glutamine Matrix Support (L-Glutamine): Administered as the primary metabolic fuel for enterocytes (intestinal epithelial cells). L-Glutamine supplementation actively drives cellular repair, reverses villous atrophy, and strengthens the tight junctions (claudin and occludin proteins) to resolve hyperpermeability ("leaky gut").
- Anti-Inflammatory Phyto-Extracts (Commiphora myrrha / Aloe vera gel): Utilized to downregulate chronic mucosal inflammation by inhibiting pro-inflammatory pathways (such as NF-kB and COX-2). Reducing this localized immune activation restores normal cellular transport architecture across the intestinal brush border.
[Targeted Mucosal Repair] ➔ Repairs Enterocytes & Restores Tight Junctions
[Chelated Zinc & Sublingual B12] ➔ Bypasses Inflamed Mucosa ➔ Systemic Cellular Saturation ("Biological KeyLock")
- Mechanism: Zinc bound to the amino acid glycine (Zinc Bisglycinate) passes through the stomach completely intact. It utilizes standard amino acid transport pathways rather than competitive mineral pathways, bypassing the damaged mucosal ion channels completely.
- Localized Action: Zinc L-Carnosine is specifically integrated for its unique ability to adhere directly to gut ulcerations and inflammatory lesions, delivering localized tissue-healing effects while simultaneously providing systemic zinc ions.
- Mechanism: Administered sublingually, Methylcobalamin is absorbed directly through the mucosal epithelium of the mouth into the jugular veins. This grants immediate entry into the systemic circulation, avoiding the entire destructive gastrointestinal tract and preventing hepatic first-pass metabolism.
- Form: The utilize of methylated cobalamin ensures that once the molecule reaches the bloodstream, it is immediately biologically active at the cellular level without requiring complex, energy-depleted enzymatic conversion steps by the host.